Welcome to KnowHow Daily!
Practical guides, money-saving tips, tech solutions, government benefits, and useful information for everyday life.
Welcome to KnowHow Daily!
Practical guides, money-saving tips, tech solutions, government benefits, and useful information for everyday life.

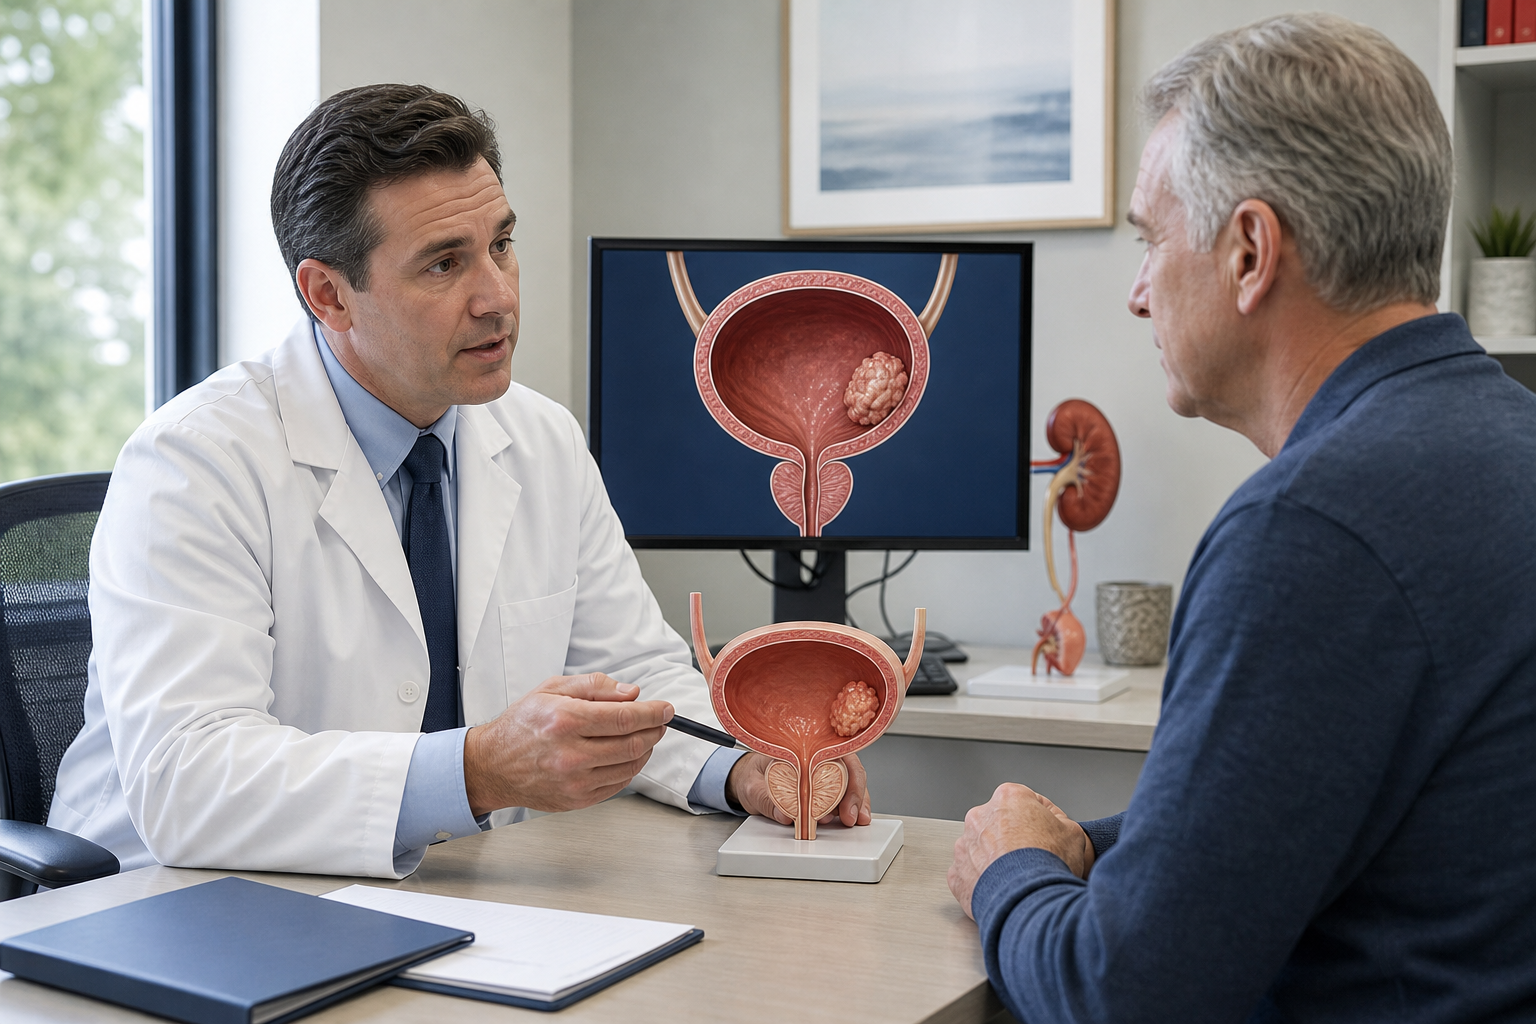
The FDA expanded Anktiva's approval on October 14, 2026, for adults with BCG-unresponsive high-grade papillary-only bladder cancer. Here's what the decision covers.
The U.S. Food and Drug Administration expanded Anktiva’s approved use on October 14, 2026. The treatment, whose generic name is nogapendekin alfa inbakicept-pmln, is now approved with Bacillus Calmette-Guérin, or BCG, for adults with BCG-unresponsive non-muscle-invasive bladder cancer that consists of high-grade papillary-only tumors.
That distinction matters. The expanded approval is not for every type of bladder cancer that has stopped responding to BCG. It covers a specific group: adults whose disease remains confined to the bladder’s inner layers, is high grade, has a papillary growth pattern without carcinoma in situ, and has not responded adequately to BCG.
The FDA previously approved Anktiva with BCG for BCG-unresponsive non-muscle-invasive bladder cancer involving carcinoma in situ, with or without papillary tumors. The October 2026 decision extends the indication to people with high-grade papillary-only disease.

A patient generally needs to fit several pieces of the diagnosis. The cancer must be:
Those details cannot be confirmed from symptoms alone. The eligibility decision depends on pathology reports, cystoscopy findings, urine cytology, prior BCG doses and timing, and whether the tumor was completely removed or resected when appropriate.
In practical terms, a person with muscle-invasive disease, metastatic disease, a different tumor grade, or a diagnosis that does not meet the formal definition of BCG-unresponsive disease may not fit this particular FDA indication.
The FDA did not base the expanded indication on a new randomized trial conducted only in patients with papillary-only tumors. Instead, the agency reviewed the earlier evidence for Anktiva in BCG-unresponsive high-risk non-muscle-invasive bladder cancer involving carcinoma in situ, then considered clinical and laboratory evidence showing important similarities between carcinoma in situ and high-grade papillary disease.
The two patterns are not identical. Papillary tumors grow in an outward, frond-like structure, while carcinoma in situ is a flat, high-grade lesion. Still, both can be aggressive, may occur together, and can carry a substantial risk of recurrence or progression after BCG no longer controls the disease.
That means the FDA’s decision supports using the existing evidence across a closely related disease group. It should not be read as proof that every patient with papillary-only bladder cancer will respond, or that the treatment has been tested in exactly the same way as a dedicated papillary-only trial.
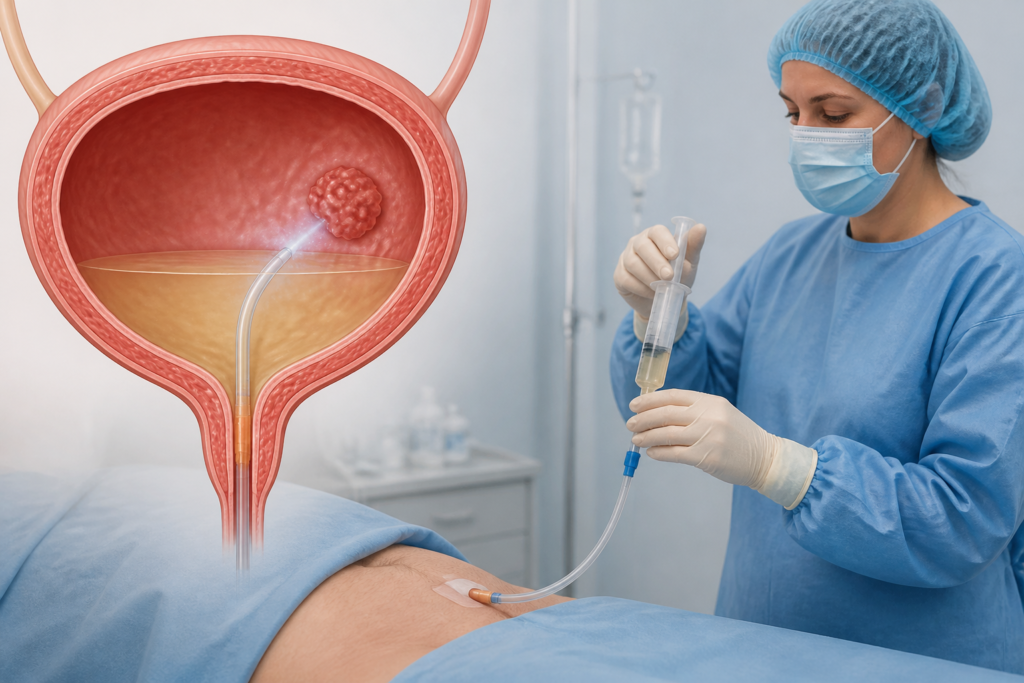
Anktiva is not a pill or an intravenous infusion. It is placed directly into the bladder through a catheter after dilution and is administered together with BCG. The liquid is held in the bladder for approximately two hours during treatment, according to FDA patient information for Anktiva.
The FDA’s recommended schedule begins with:
The maximum treatment duration is 37 months. Treatment should be stopped if disease persists after the second induction course, returns or progresses, or side effects become unacceptable.
Follow-up is a central part of this treatment. Doctors use cystoscopy to look inside the bladder, urine cytology to check for abnormal cells, and sometimes biopsy or tumor resection to clarify whether high-grade disease remains.
The three-month assessment is especially important because it helps determine whether another induction course is appropriate. Later findings guide maintenance treatment and can change the overall plan if the cancer returns, progresses, or cannot be controlled safely.
A complete response means that no high-grade cancer is detected during the relevant follow-up assessments. It does not mean the risk of recurrence has disappeared, which is why continued surveillance remains necessary.
Anktiva offers another bladder-preserving treatment option for a narrowly defined group, but it is not a general replacement for surgery. The FDA-approved prescribing information includes a warning that delaying cystectomy can allow bladder cancer to become metastatic, and metastatic disease can be fatal.
That warning is particularly important when high-grade disease persists or returns. Some patients may reasonably discuss bladder-preserving treatment with their urologist, while others may be advised that earlier cystectomy offers a better chance of controlling the cancer. The decision depends on tumor features, previous treatment, overall health, surgical risk, personal priorities, and how the disease responds over time.
Patients should ask their urology team what the recommended surgical alternative would be, how long it is safe to continue bladder-preserving treatment, and which test results would trigger a change in plan. Choosing Anktiva should involve a clear monitoring and contingency plan rather than an open-ended delay.
The FDA lists painful urination, frequent urination, urinary urgency, blood in the urine, urinary tract infection, muscle or joint pain, chills, fever, and increased creatinine or potassium among the more common adverse reactions and laboratory abnormalities.
Some urinary symptoms can overlap with expected bladder irritation from BCG, but new, severe, persistent, or worsening symptoms should be reported promptly. The treating team may need to check for infection, treatment-related inflammation, kidney or electrolyte changes, or evidence that the cancer is progressing.
The October 14, 2026, approval is a U.S. FDA decision. It does not by itself establish authorization, reimbursement, or availability in Canada. Canadian patients and caregivers should verify the product’s status through Health Canada’s Drug Product Database and discuss locally available options with a Canadian urologist or oncologist.
Check Health Canada’s Drug Product DatabaseFor an individual patient, the most useful next step is a detailed review of the pathology, BCG history, cystoscopy findings, and treatment alternatives with a bladder-cancer specialist.
A. No. Anktiva is an approved bladder-preserving option for a specific group of adults with BCG-unresponsive, high-grade papillary-only non-muscle-invasive bladder cancer. FDA labeling warns that delaying cystectomy can allow metastatic bladder cancer to develop, so surgery should remain part of the treatment discussion.
A. The FDA’s expanded decision relied on earlier Anktiva efficacy data in BCG-unresponsive disease involving carcinoma in situ, together with clinical and laboratory similarities between carcinoma in situ and high-grade papillary tumors. The FDA did not describe the expansion as the result of a new dedicated papillary-only randomized trial.
A. The FDA schedule begins with six weekly induction treatments, may include a second six-week induction course, and can include maintenance courses through month 37. Treatment should stop if disease persists after the second induction, returns or progresses, or side effects become unacceptable.
A. No. A U.S. FDA approval does not automatically authorize a medicine for sale or reimbursement in Canada. Canadian patients should check Health Canada’s Drug Product Database and speak with a Canadian oncology or urology team about authorization, access, and alternatives.









FDA Infant Formula Standards Proposal: What Parents Need to Know About Nutrient Changes and the Comment Deadline